
Home / 2026 Medicare Supervision Rules for Mental Health
If you bill Medicare Part B for mental health services in 2026, one fact drives payment: your record must show the right supervision happened at the right time.
Medicare still lets many Part B services use virtual direct supervision in 2026, but only through live two-way audio/video.
Audio-only does not count.
And if your notes, supervision logs, treatment plans, or incident-to support are missing, a paid claim can still be denied later or taken back.
WHAT’S IMPORTANT:
Direct supervision = immediate availability, not same-room presence
Virtual direct supervision is allowed for many office and outpatient Part B services
FQHCs and RHCs follow different supervision rules than physician offices and outpatient clinics
Incident-to billing still needs full chart support, not just a statement that supervision occurred
Telehealth care and virtual supervision are separate items and should be documented separately
Audit risk is highest when logs, treatment plans, coding, scope-of-practice support, or billing NPIs are wrong
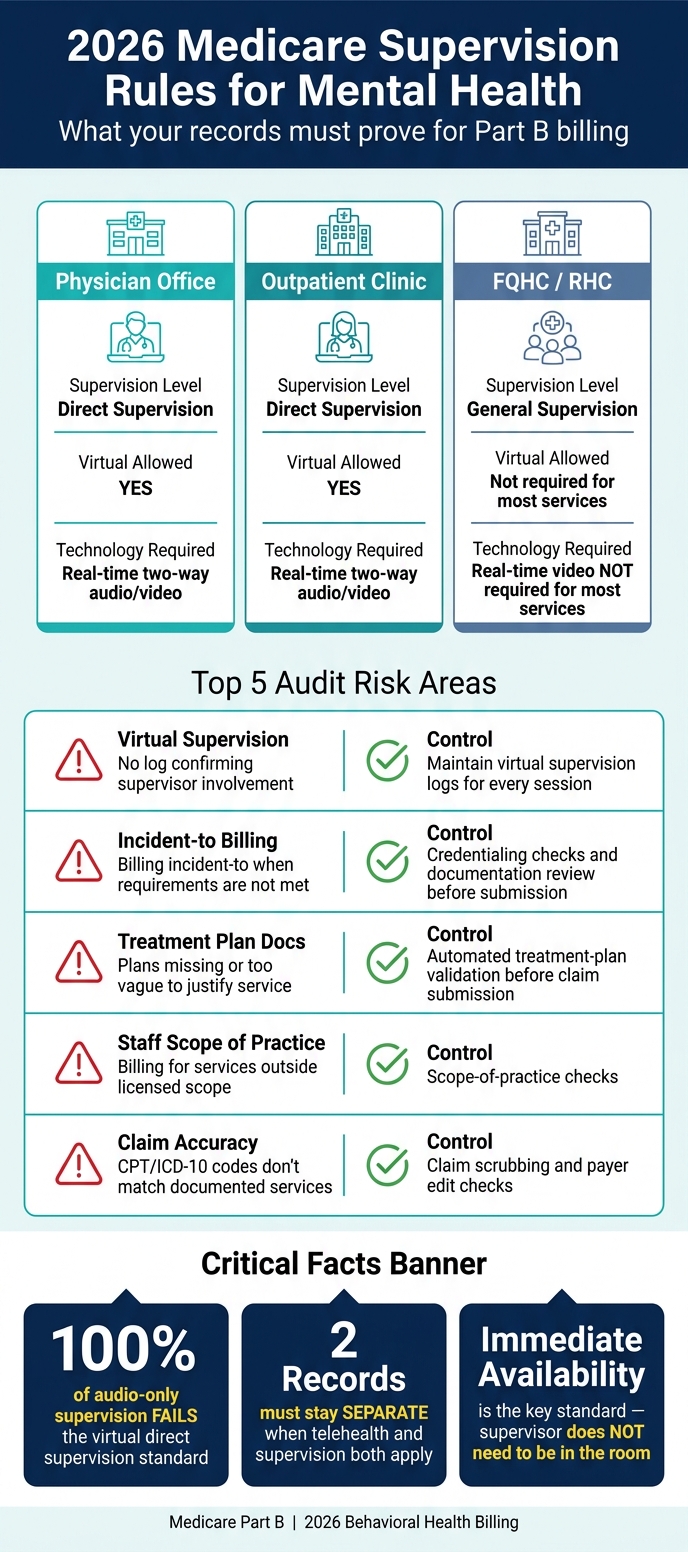
100% of audio-only supervision fails the virtual direct supervision standard, and 2 records must stay separate when telehealth and supervision both apply – the patient visit record and the supervision record.
2026 Medicare Supervision Rules for Mental Health: Key Requirements by Setting
Area | What Medicare expects in 2026 | Main mistake |
|---|---|---|
Direct supervision | Supervisor can help without delay | No proof the supervisor was available |
Virtual supervision | Live two-way audio/video | Using audio-only |
Incident-to billing | Full support in the chart | Assuming supervision alone makes it billable |
Telehealth + supervision | Separate documentation for each | Blending the two together |
Audit support | Logs, treatment plans, coding, scope checks | Missing or vague records |
Bottom line: Treat supervision as a billing rule first and a workflow issue second. If the chart cannot prove compliance, the claim is exposed.
The key rule in 2026 is immediate availability. Direct supervision means the supervising practitioner must be able to give help and direction during the service without delay. They do not need to be in the room.
That sounds simple, but the day-to-day effect can change based on the setting, staffing model, and whether the service is billed incident-to.
For office and outpatient billing, practices need to document that the supervisor could step in right away if needed. That point decides whether the claim meets Medicare supervision rules.
Put plainly: if the record doesn’t show the supervisor was available at the time of service, the claim can run into trouble even if the care itself was delivered properly.
Medicare allows real-time, two-way audio/video to meet direct supervision rules for many Part B services. Audio-only communication does not count.
So, a live video connection can work. A phone call by itself can’t.
The setting drives which supervision level applies. And that, in turn, shapes what the claim needs to support. Here’s how the rules differ across common behavioral health billing sites:
Setting | Supervision Standard | Technology Requirement |
|---|---|---|
Physician Office | Direct supervision; virtual allowed | Real-time two-way audio/video |
Outpatient Clinic | Direct supervision; virtual allowed | Real-time two-way audio/video |
General supervision (for most behavioral health services) | General supervision; real-time video not required for most services |
FQHCs and RHCs work under a different reimbursement framework than physician offices and outpatient clinics. That changes how claims are built and what the documentation must show.
Before billing across sites, confirm the supervision level for each location. Then document the supervisor’s availability and the technology used. If that record is missing, Medicare may deny payment or recoup it later, even when supervision did happen.
These site-based rules matter most when auxiliary staff bill incident-to, which the next section addresses.
Incident-to billing in 2026 still comes down to a few basic things: complete documentation, correct coding, and clear supervision records. That last piece matters even more when auxiliary staff are involved.
The main rules haven’t changed. The chart needs to support the service, the code needs to fit what was done, and the practice needs to follow payer rules all the way through.
Keep clinical documentation accurate and complete.
Use the correct CPT, ICD-10, or HCPCS code.
Document supervision and practitioner involvement clearly.
Auxiliary behavioral health staff can be billed only when the service, supervision, and documentation all support incident-to billing. That’s where many practices slip. It’s not enough to say supervision happened. The claim file has to show it.
A common mix-up is thinking supervision by itself makes a claim billable. It doesn’t. The usual problems include:
submitting claims with incomplete documentation
billing the wrong code for the service
skipping eligibility checks
missing required prior authorization
Even when the care was appropriate, these mistakes can trigger denials, extra rework, and audit exposure.
Scenario | What still matters in 2026 | Common billing risk |
|---|---|---|
Standard incident-to billing | Accurate documentation, correct coding, and a supportable claim record | Claim denial if the record does not support the service |
Behavioral health services furnished by auxiliary staff | Clear supervision documentation and complete clinical notes | Audit exposure from incomplete or unclear records |
Virtual supervision may change the day-to-day workflow, but the record still needs to prove it.
When telehealth and incident-to billing show up in the same claim, the chart needs to spell out two separate things: the patient visit and the supervision method.
A telehealth visit is remote care for the patient. Virtual direct supervision is remote oversight by the supervising practitioner during the service. Those are not the same thing, and the record should treat them that way.
If the chart blends them together, billing can get messy fast. Keeping them separate helps avoid confusion and cuts down the chance of claim denials.
Virtual supervision adds one more documentation step: the telehealth encounter and the supervision record need to stay separate [1].
That means your EMR workflow should do some of the heavy lifting. Route signatures where they need to go. Flag missing supervision notes before the claim moves forward. The goal is simple: make sure the encounter record and the supervision record are both complete, but not mixed together.
Scenario | What it means | Documentation focus |
|---|---|---|
Telehealth visit | The patient receives care remotely. | Record the encounter clearly as telehealth. |
Virtual direct supervision | The supervising practitioner supervises the service through real-time audio/video technology. | Keep the supervision arrangement clearly documented. |
EMR workflow | Supports telehealth and supervision billing. | Use EMR workflows that support automated signature routing and compliance checks [2]. |
Telehealth and virtual supervision do different jobs in billing, so the chart has to keep them apart. That split matters most when Medicare reviews claims tied to supervision or incident-to billing. Clear records can lower Medicare audit risk.
When supervision and incident-to rules are in place, the next issue is simple: can the chart prove it?
In 2026, Medicare audits most often flag missing supervision logs, weak treatment plans, scope-of-practice errors, and incident-to claims billed under the wrong NPI. Incomplete treatment plans can fail medical-necessity review. Services billed outside a staff member’s licensed scope often lead to denial or recoupment. And when those problems pile up, they don’t just hurt compliance – they slow cash flow, add repayment demands, and create more appeals work for the revenue cycle team [1].
These are the main failure points and the controls that help prevent them.
Risk Area | Rule | Common error | Recommended Internal Control |
|---|---|---|---|
Virtual supervision | Documentation should show that supervision was properly provided | No log confirming the supervising practitioner’s involvement | Maintain virtual supervision logs for every session |
Incident-to billing | The service must meet incident-to requirements and stay within scope of practice | Billing incident-to when the claim does not satisfy those requirements | Credentialing checks and documentation review before submission |
Treatment plan documentation | Records must support medical necessity | Plans that are missing or too vague to justify the service | Automated treatment-plan validation before claim submission |
Staff scope of practice | Services must fall within the supervising and supervised staff’s licensed scope | Billing for services the supervised clinician is not licensed to provide | Scope-of-practice checks |
Claim accuracy | CPT and ICD-10 codes must match documented services | Codes that do not match the documented service | Claim scrubbing and payer edit checks |
Point-of-care documentation is your first line of defense against denials and recoupment.
That means supervision records, treatment plans, and encounter notes should be complete before a claim goes out the door. A missing log or vague plan might seem minor in the moment, but it can turn into a denied claim later.
Focus on a few core controls:
Supervision logs
Treatment-plan checks
Claim scrubbing
Denial tracking before submission
Done well, these steps help catch billing issues before Medicare does.
The available information does not spell out chart documentation or proof standards for Medicare virtual supervision in 2026.
If you need help with documentation and compliance, BHRev works with behavioral health providers to sort through payer rules, documentation requirements, and changing compliance standards so they can cut denial risk.
In 2026, mental health services may be billed incident-to when they’re an integral, though incidental, part of a physician’s or non-physician practitioner’s professional services.
To qualify, the services must be provided in the billing provider’s office by auxiliary staff under direct supervision. That means the billing practitioner must be immediately available to give assistance and direction for the full service.
No. Federally Qualified Health Centers (FQHCs) and Rural Health Clinics (RHCs) follow different Medicare billing and supervision rules than standard physician offices.
That means the incident-to and general supervision rules used in private practice do not automatically apply here. For behavioral health providers, the safest move is simple: check official Medicare guidance and make sure your billing and supervision setup matches those rules.
One email a month, no fluff. Unsubscribe anytime.