Home / Claim Scrubbing vs. Validation: Key Differences
BLOG
Claim Scrubbing vs. Validation: Key Differences
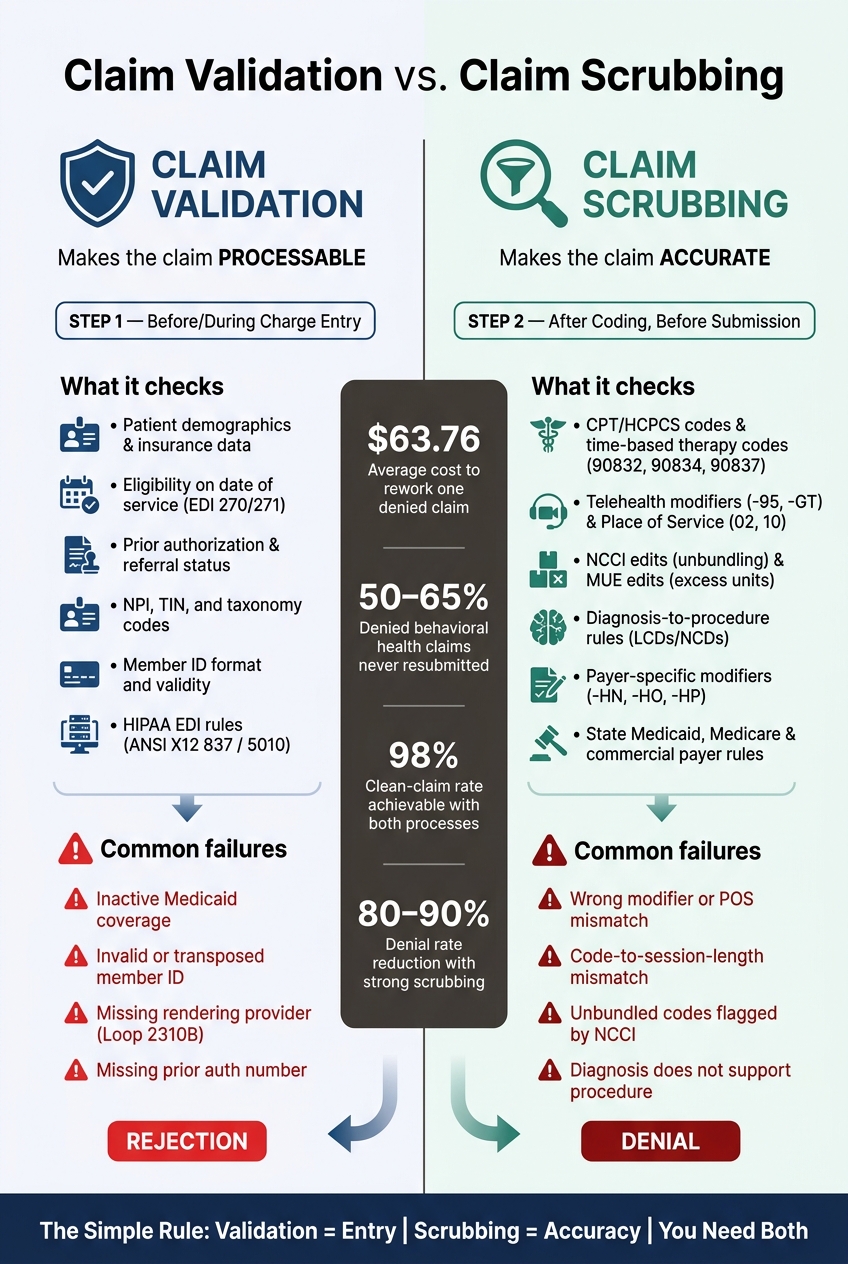
Shows how validation ensures claims are processable and scrubbing ensures coding accuracy to prevent rejections and denials.
SHARE
Mix up claim validation and claim scrubbing, and you can end up sending claims that look clean on paper but still come back denied.
The difference is simple once you see it: validation checks whether a claim can even enter the payer’s system, while scrubbing checks whether the claim is coded and built correctly before it goes out the door.
That distinction is worth getting right — reworking a denied claim costs about $63.76 on average, and in behavioral health specifically, 50% to 65% of denied claims never even get resubmitted.
SUMMARY:
Validation comes first
checks patient and insurance data
confirms coverage on the date of service
reviews authorization, referrals, and provider enrollment
looks for front-end issues like invalid member IDs or missing rendering provider data
Scrubbing comes after coding
checks CPT/HCPCS coding
reviews modifiers like -95 and -GT
checks place of service such as 02 and 10
applies payer edits like NCCI, MUE, and diagnosis-to-procedure rules
They stop different problems. Validation helps stop rejections. Scrubbing helps stop denials.
They stop different problems
validation helps stop rejections
scrubbing helps stop denials
Claim Validation vs. Claim Scrubbing: Key Differences in Healthcare Billing
Quick Comparison
Check
Validation
Scrubbing
Main job
Makes sure the claim is processable
Makes sure the claim is accurate for billing
When it happens
Before or during charge entry
After coding, before submission
Looks at
Eligibility, demographics, authorization, provider data
Codes, modifiers, POS, payer edits, medical need rules
Common failure
Inactive coverage, bad member ID, missing auth
Wrong code, wrong modifier, POS mismatch, unit errors
Main result if missed
Rejection
Denial
The simplest way to think about it is: validation is about entry, scrubbing is about accuracy.You need both if you want cleaner claims, fewer billing errors, and fewer delays in payment.
What Claim Validation Checks Before a Claim Can Be Processed
Claim validation is the first gate a claim has to clear before it ever reaches a payer. Validation checks whether a claim is processable. Scrubbing comes after that and checks whether the claim is accurate enough to submit.
Put simply, validation asks: Can this claim move through the system at all? It checks that required fields are filled in, identifiers use the right format, and the transaction meets HIPAA EDI rules, including ANSI X12 837 and 5010.[9][10] That happens before scrubbing, which focuses on coding and claim accuracy instead of basic processability.
Data Integrity, Eligibility, and Authorization Checks
Validation checks that patient demographics, insurance data, and provider identifiers are complete and formatted the right way. On the provider side, it verifies the National Provider Identifier (NPI), Tax Identification Number (TIN), and taxonomy codes to confirm the provider is enrolled with the payer.
It also checks whether insurance coverage was active on the date of service through real-time EDI 270/271 eligibility transactions. From there, validation looks at active coverage, benefits, coordination-of-benefits status, prior authorization, and referral rules to confirm they line up with the service billed.[9][5] It also confirms that units and totals match.
Those checks matter more than they may seem at first glance. Eligibility and demographic mistakes account for nearly 20% of all rejected claims, and missing or inaccurate claim data drives 50% of all claim denials.[2][4] So this step isn’t just admin busywork. It’s the first screen that keeps avoidable rejections from piling up.
Behavioral Health Examples of Validation Failures
In behavioral health billing, validation failures usually show up in a small set of recurring problems. One of the most common is inactive Medicaid coverage. If a patient’s coverage has lapsed, the claim can be rejected right away. Invalid member IDs are another frequent issue. A single transposed digit or the wrong policy format can trigger an immediate front-end rejection.[5][9][12]
Missing rendering provider information can also stop the claim cold. In the X12 837P file, if Loop 2310B – the rendering provider loop – isn’t populated, the claim gets rejected before any coding review begins. The same goes for services such as IOP and PHP: submitting the claim without a valid prior authorization number can lead straight to rejection.[10][5][11]
In behavioral health, these problems block the claim before coding edits even come into play. They’re front-end failures, plain and simple.
Once validation clears, scrubbing takes over to check coding, modifiers, and payer-rule edits before submission.
What Claim Scrubbing Checks Before Submission to the Payer
Once validation shows a claim can move through the system, scrubbing checks whether it should be sent at all. That means looking for coding mistakes, missing pieces, and payer-specific edits that may slip past intake checks but still lead to a denial later. In behavioral health, those problems usually come down to code, modifier, or payer-rule mismatches.
Behavioral Health Coding and Payer-Rule Edits
Behavioral health billing gets denied a lot. Scrubbing helps catch that early by checking that therapy codes match the documented time and are paired the right way [2][8]. With time-based codes like 90832, 90834, and 90837, even a small gap between the code billed and the session length in the chart can trigger a denial.
Telehealth adds another layer. Scrubbing should verify modifier -95 or -GT, along with the right place of service: 02 for services provided outside the home and 10 for services provided in the home [2][6]. If a claim uses POS 11 for telehealth or PHP/IOP services, that creates a mismatch that basic validation may not catch [6]. And that’s just one part of the review. The payer’s own rules still decide whether the claim gets paid.
Scrubbing also applies NCCI edits to stop unbundling and MUE edits to flag excess units [4][5]. It checks whether the diagnosis supports the procedure under LCDs and NCDs [4][5]. Then payer-specific rules come into play. State Medicaid programs, Medicare, and commercial payers may each require different modifiers, provider-level modifiers such as -HN, -HO, and -HP, and different attachments [4][6].
How Automation Supports Scrubbing in Behavioral Health RCM
Manual review can only go so far. It takes time, and it often misses repeat issues hiding across batches of claims. Automated rules engines can check modifier logic, POS alignment, diagnosis-to-procedure fit, and payer-specific requirements in a single pass. AI-powered systems take it a step further by looking at past denial patterns and flagging high-risk claims that pass static rules but still have a strong chance of being denied based on how a payer has behaved over time [1][4]. That gives teams more consistent checks across coding, modifiers, and payer rules than manual review can deliver on its own.
BHRev provides AI-powered claim scrubbing for behavioral health providers, including Medicaid and payer-specific rule support. That’s why the gap between validation and scrubbing matters for denial prevention.
Claim Scrubbing vs. Validation: Key Differences That Affect Denials
Once the basics are clear, the main point is where each check happens in the workflow. Validation and scrubbing catch different problems at different times. That gap is exactly why you need both.
Purpose, Timing, and Depth of Review
Validation happens early – during registration, scheduling, or charge entry. Its role is to confirm coverage, provider data, and authorization.
Scrubbing happens later, after coding is done and the claim is almost ready to go out. At that stage, the focus shifts to the coded claim and payer-specific logic. Are the codes matched the right way? Does the diagnosis support the procedure? Are the correct modifiers in place?
Dimension
Claim Validation
Claim Scrubbing
Primary Purpose
Confirms baseline processability and eligibility
Ensures coding accuracy and payer-rule compliance
Timing
Early: registration, scheduling, or charge entry
Late: post-coding, immediately before submission
Depth of Review
Data integrity, insurance status, provider enrollment
NCCI/MUE edits, modifier logic, medical necessity
Denial Types Each Process Helps Prevent
When validation fails, the result is usually a rejection. Common causes include inactive coverage, missing authorizations, invalid member IDs, and credentialing mismatches.
In behavioral health, this can look pretty familiar: a visit gets scheduled with a provider who is not credentialed for a specific Medicaid program, or intake misses a mental health carve-out payer.
Scrubbing failures show up later as denials after submission. These issues often involve coding errors, modifier misuse, place-of-service conflicts, and diagnosis-to-procedure mismatches that made it past intake but did not pass adjudication.
Put simply, these two steps act as a pre-submission filter. The next step is building them into one workflow.
How to Use Both Processes Together in a Behavioral Health Workflow
Once the difference is clear, the next move is to put both checks in the right order. Validation and scrubbing do their best work when they happen in sequence.
Start by collecting accurate demographic and insurance details at registration. Before care is delivered, verify eligibility and authorization. After that, code the claim from complete documentation. Then validate the data and scrub the coding before the claim goes to the clearinghouse.
Each step goes after a different point of failure, from eligibility rejections to coding denials.
That order matters. Every issue caught upstream means less cleanup later.
Measurable Outcomes and Platform Support
When teams treat validation and scrubbing as two separate checks, clean-claim rates can move toward 98%[3]. On the flip side, weak first-pass quality can stretch days in A/R from 45 to more than 58[7]. And strong scrubbing can cut denial rates by 80% to 90%[5].
One platform can handle both layers of review. BHRev supports both steps with automated eligibility verification and AI-powered claim scrubbing for behavioral health billing. For providers billing Medicaid, Medicare, and commercial plans, using one platform can help close the gaps between validation and scrubbing.
Conclusion: Validation Makes Claims Processable, Scrubbing Makes Them Accurate
The takeaway is straightforward: process first, precision second. Validation checks that a claim can get into the payer’s system. Scrubbing checks that the claim lines up with coding rules and payer requirements. Behavioral health providers need both steps as a two-part defense for revenue and compliance.
FAQs
Can a claim pass validation and still be denied?
Yes. A claim can pass validation and still be denied.
Validation means the claim is set up the right way. It’s complete, follows format rules, and uses the right codes. But that doesn’t guarantee payment.
A denial can still happen during payer adjudication if the payer finds issues that basic validation doesn’t catch, such as:
expired prior authorization
eligibility problems
medical necessity disputes
contract-level reimbursement rules
Who should own validation vs. scrubbing?
Ownership should be shared between technology and human know-how. Automated claim scrubbing tools can take the first pass, checking coding, demographics, and payer-specific rules.
But the final quality audit should stay with experienced medical billers and coders. Software can miss details like diagnosis-to-service alignment and authorization requirements.
How often should payer-specific scrubbing rules be updated?
Payer-specific scrubbing rules need regular updates to match changing requirements. Manual review helps, but on its own, it can miss frequent rule changes. That’s why automated systems should be part of the process, so they can respond to new denial patterns as they show up.
Medical codes also need to be audited quarterly against the latest CMS and AMA updates. And when the same denial reasons keep showing up, that feedback should go straight back into the scrubbing process so your rules can be refined without delay.