Why behavioral health is different
If you only check denials, you are likely missing paid claims that were still paid short.
In behavioral health, that gap can cost 5% to 8% of yearly revenue, and high-volume codes like CPT 90837 can make small misses add up fast.
Three things to look for in an RCM tool:
How they check contract terms
When they flag short payments
How much appeal work they help with
This article covers BHRev, Waystar, FinThrive, MD Clarity RevFind, R1 RCM, and Experian Health. Some are built for behavioral health teams, while others fit large multi-site groups that need more contract review and recovery support.
QUICK COMPARISON:
BHRev: best match for behavioral health-first billing and recovery
Waystar: strong for high claim volume and broad payer reach
FinThrive: focused on contract pricing control and variance review
RevFind: deep line-level payment checking
R1 RCM: geared toward large-system recovery workflows
Experian Health: focused on contract monitoring and bulk appeals
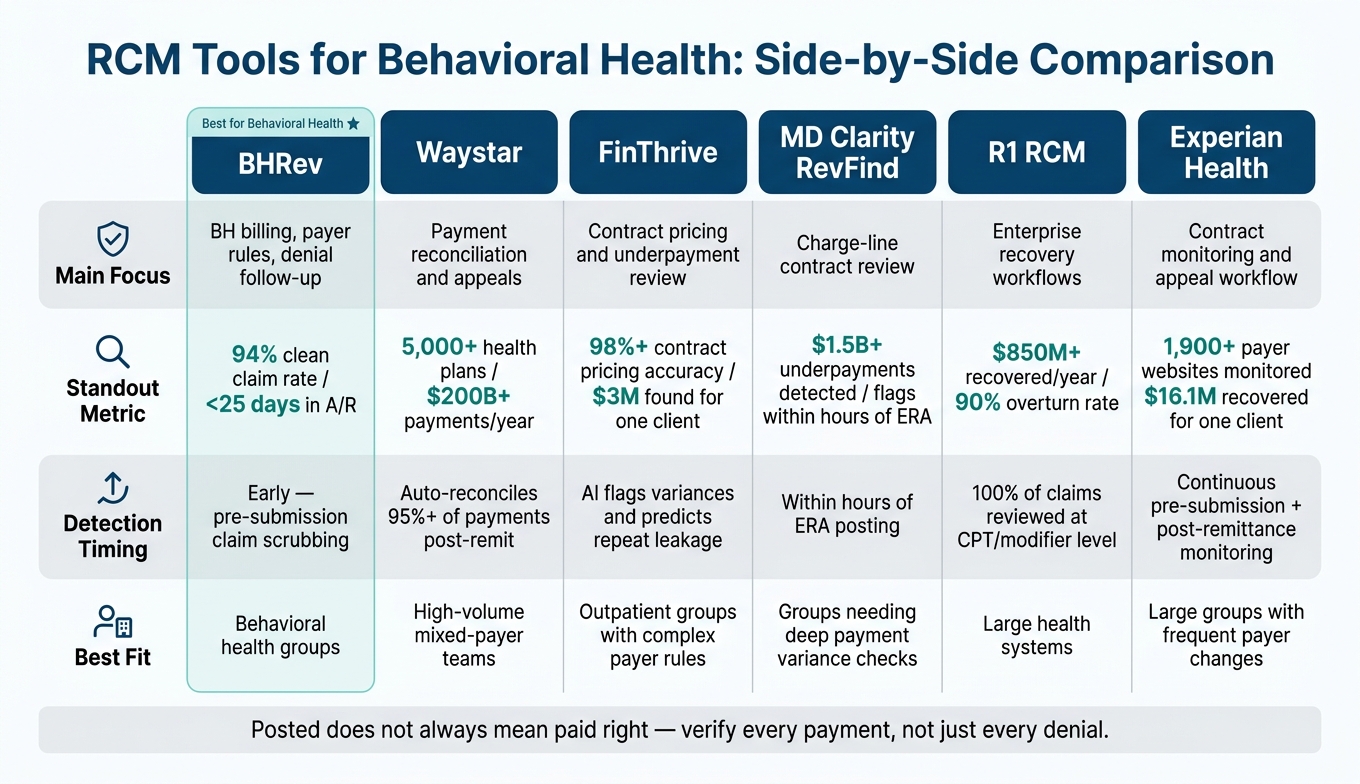
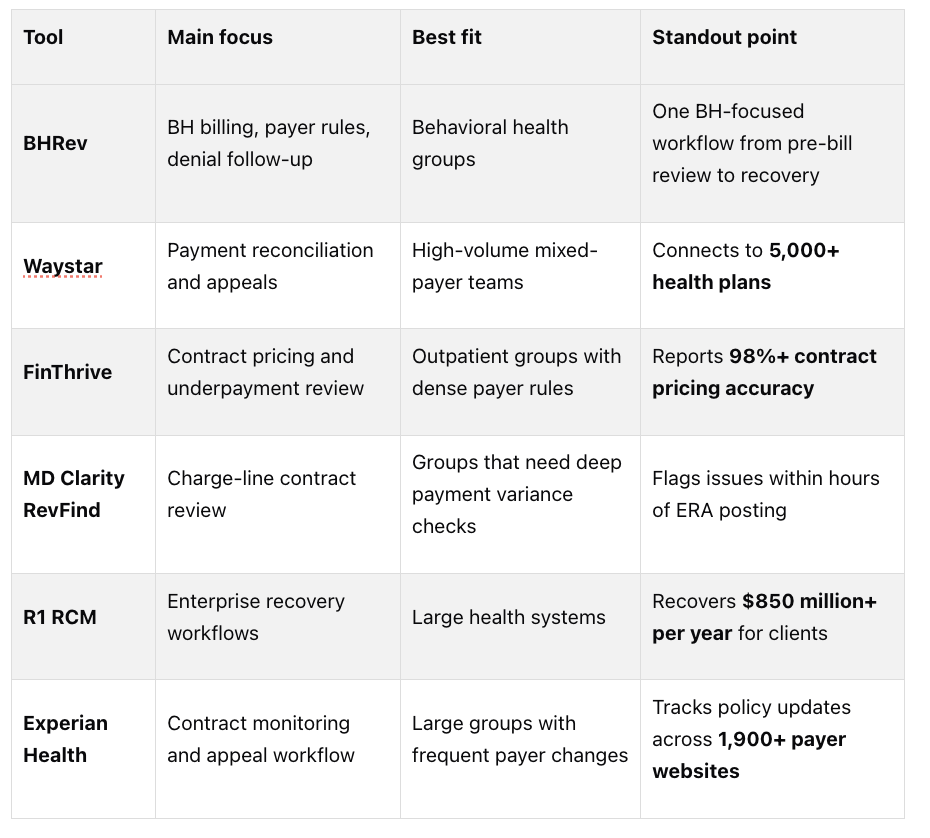
The bottom line: posted does not always mean paid right.
Use this guide to figure out which tool helps you catch short pays early, prove the variance, and push recovery before filing windows close.
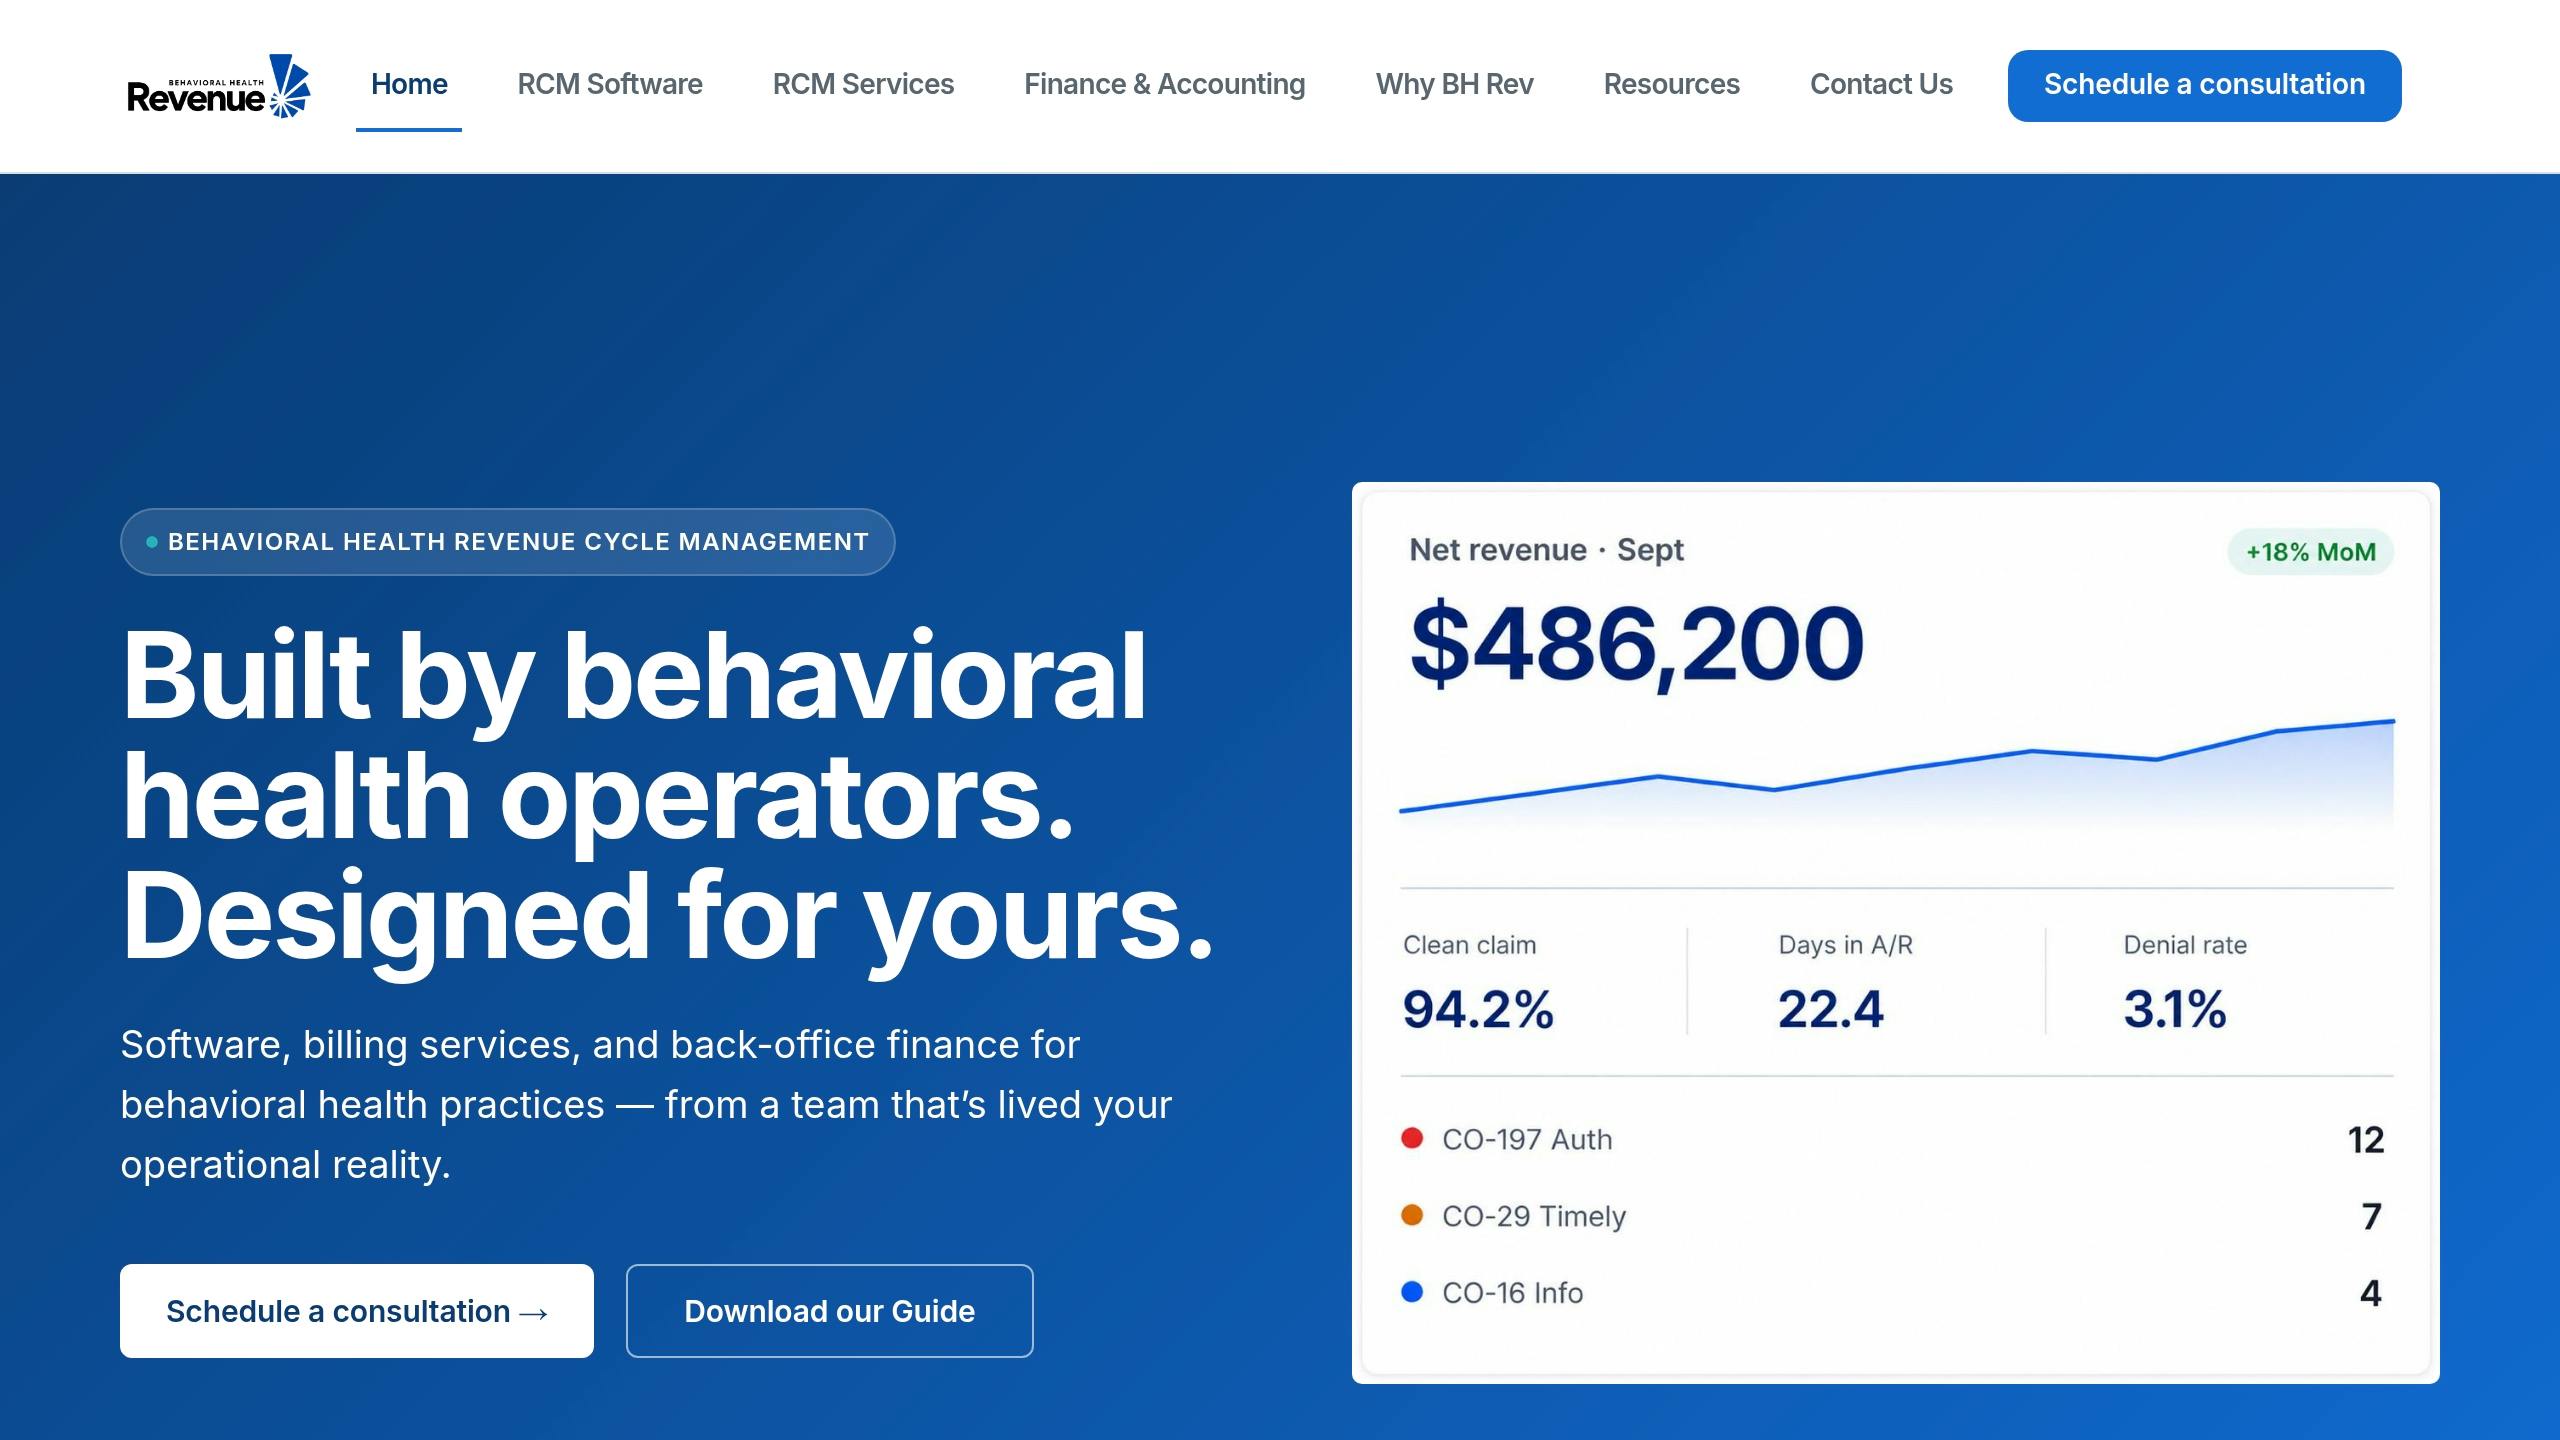
BHRev is built for behavioral health billing, payer rules, and revenue cycle management. That focus matters when claim edits, payment review, and denial follow-up need to function as one connected process.[1]
Contract Reconciliation
BHRev uses claim scrubbing to check claims against payer-specific requirements before submission. The platform also connects directly to partner EHRs, so clinical data and billing rules stay in sync in real time.[1]
Underpayment Detection
BHRev’s live A/R, denial, and payer dashboards help practices spot reimbursement variances and underpayments in aged A/R. Put simply, teams can see where money may be missing instead of digging through reports after the fact. BHRev reports an average 94% clean claim rate for practices on its platform.[1]
Appeals Workflow
Once payment is posted, the job shifts from prevention to recovery. BHRev uses denial workflows and BH-specific denial playbooks to support follow-up and recovery on underpaid claims. Clients using BHRev’s full-service RCM support typically see fewer than 25 days in A/R.[1]
Behavioral Health Fit
BHRev offers software, outsourced billing, and finance support for behavioral health teams. That means practices can handle pre-bill compliance, post-payment review, and recovery inside one BH-focused system.[1]
2. Waystar
Waystar is built for high-volume payment reconciliation, denial recovery, and appeals across both commercial and government payers. It processes more than $200 billion in provider payments each year and connects to 5,000+ health plans, including Medicaid and Medicare.[2] Its biggest edge is simple: it handles reconciliation at scale while also supporting payer-specific recovery work.
Contract Reconciliation
Waystar’s Remit Manager automatically matches claims to remittances and flags missing or inaccurate details. The platform auto-reconciles and posts more than 95% of payer payments. It can also turn paper explanations of benefits (EOBs) into searchable 835 files, which cuts paper-handling cost per claim and helps teams spot contract variances before they age out.[2]
Underpayment Detection
For Medicare underpayments, Waystar’s Transfer DRG solution reviews all 280 DRGs subject to PACT rules. Using CMS network data, it relies on the Common Working File (CWF) and Medicare Administrative Contractor (MAC) portals as primary data sources to find errors in discharge status and condition codes. That helps catch short pays that routine posting can miss.[3]
The service uses a contingency-based pricing model.[3] That makes it a solid fit for organizations that want both Medicare underpayment detection and follow-through.
Appeals Workflow
Waystar’s Denial + Appeal Management tool ranks denials based on which ones are most likely to overturn. It also drafts appeal letters with AltitudeAI™ and supports 1,000+ payer-specific forms.[4]
Behavioral Health Fit
Its rule-based workflows for exceptions, along with EHR, HIS, and PM integrations, support mixed-payer behavioral health operations.[4] For behavioral health teams, the upside is scale: one workflow can cover remittance review, underpayment recovery, and appeals.
3. FinThrive
FinThrive leans on subject-matter experts to handle contract loading, upkeep, and payer-specific rules.[6] That gives teams tighter control over contracts without piling on more manual review.
Contract Reconciliation
FinThrive Fusion keeps pricing aligned across estimates, claims, and underpayment review by matching expected payments against remittances and showing line-item variances.[5][7] FinThrive reports 98%+ contract pricing accuracy across all payers, including government contracts.[5]
Underpayment Detection
FinThrive’s Denials and Underpayments Analyzer uses AI to flag variances, spot patterns, and predict repeat leakage.[7] That’s a big deal when payers apply dense contract terms across high-volume outpatient claims.
Pennsylvania Mountains Healthcare Alliance identified $3 million in underpayments in its first year, which gave the team defensible data to challenge payer inaccuracies directly.[8]
Appeals Workflow
FinThrive connects underpayment findings straight into claims workflows, shortening the path from detection to appeal.[7] It also supports contract modeling and contract scenarios, so providers can test payer terms before negotiations.[5][7]
Behavioral Health Fit
These controls matter most when behavioral health billing depends on recurring visits, authorization rules, and bundled payment structures. For outpatient behavioral health, FinThrive’s episode and bundled-payment modeling helps teams track reimbursement for IOPs and recurring service lines.[10] Its prior-auth rules and government reimbursement tools also support authorization control and audit defense.[8][9]
4. MD Clarity RevFind
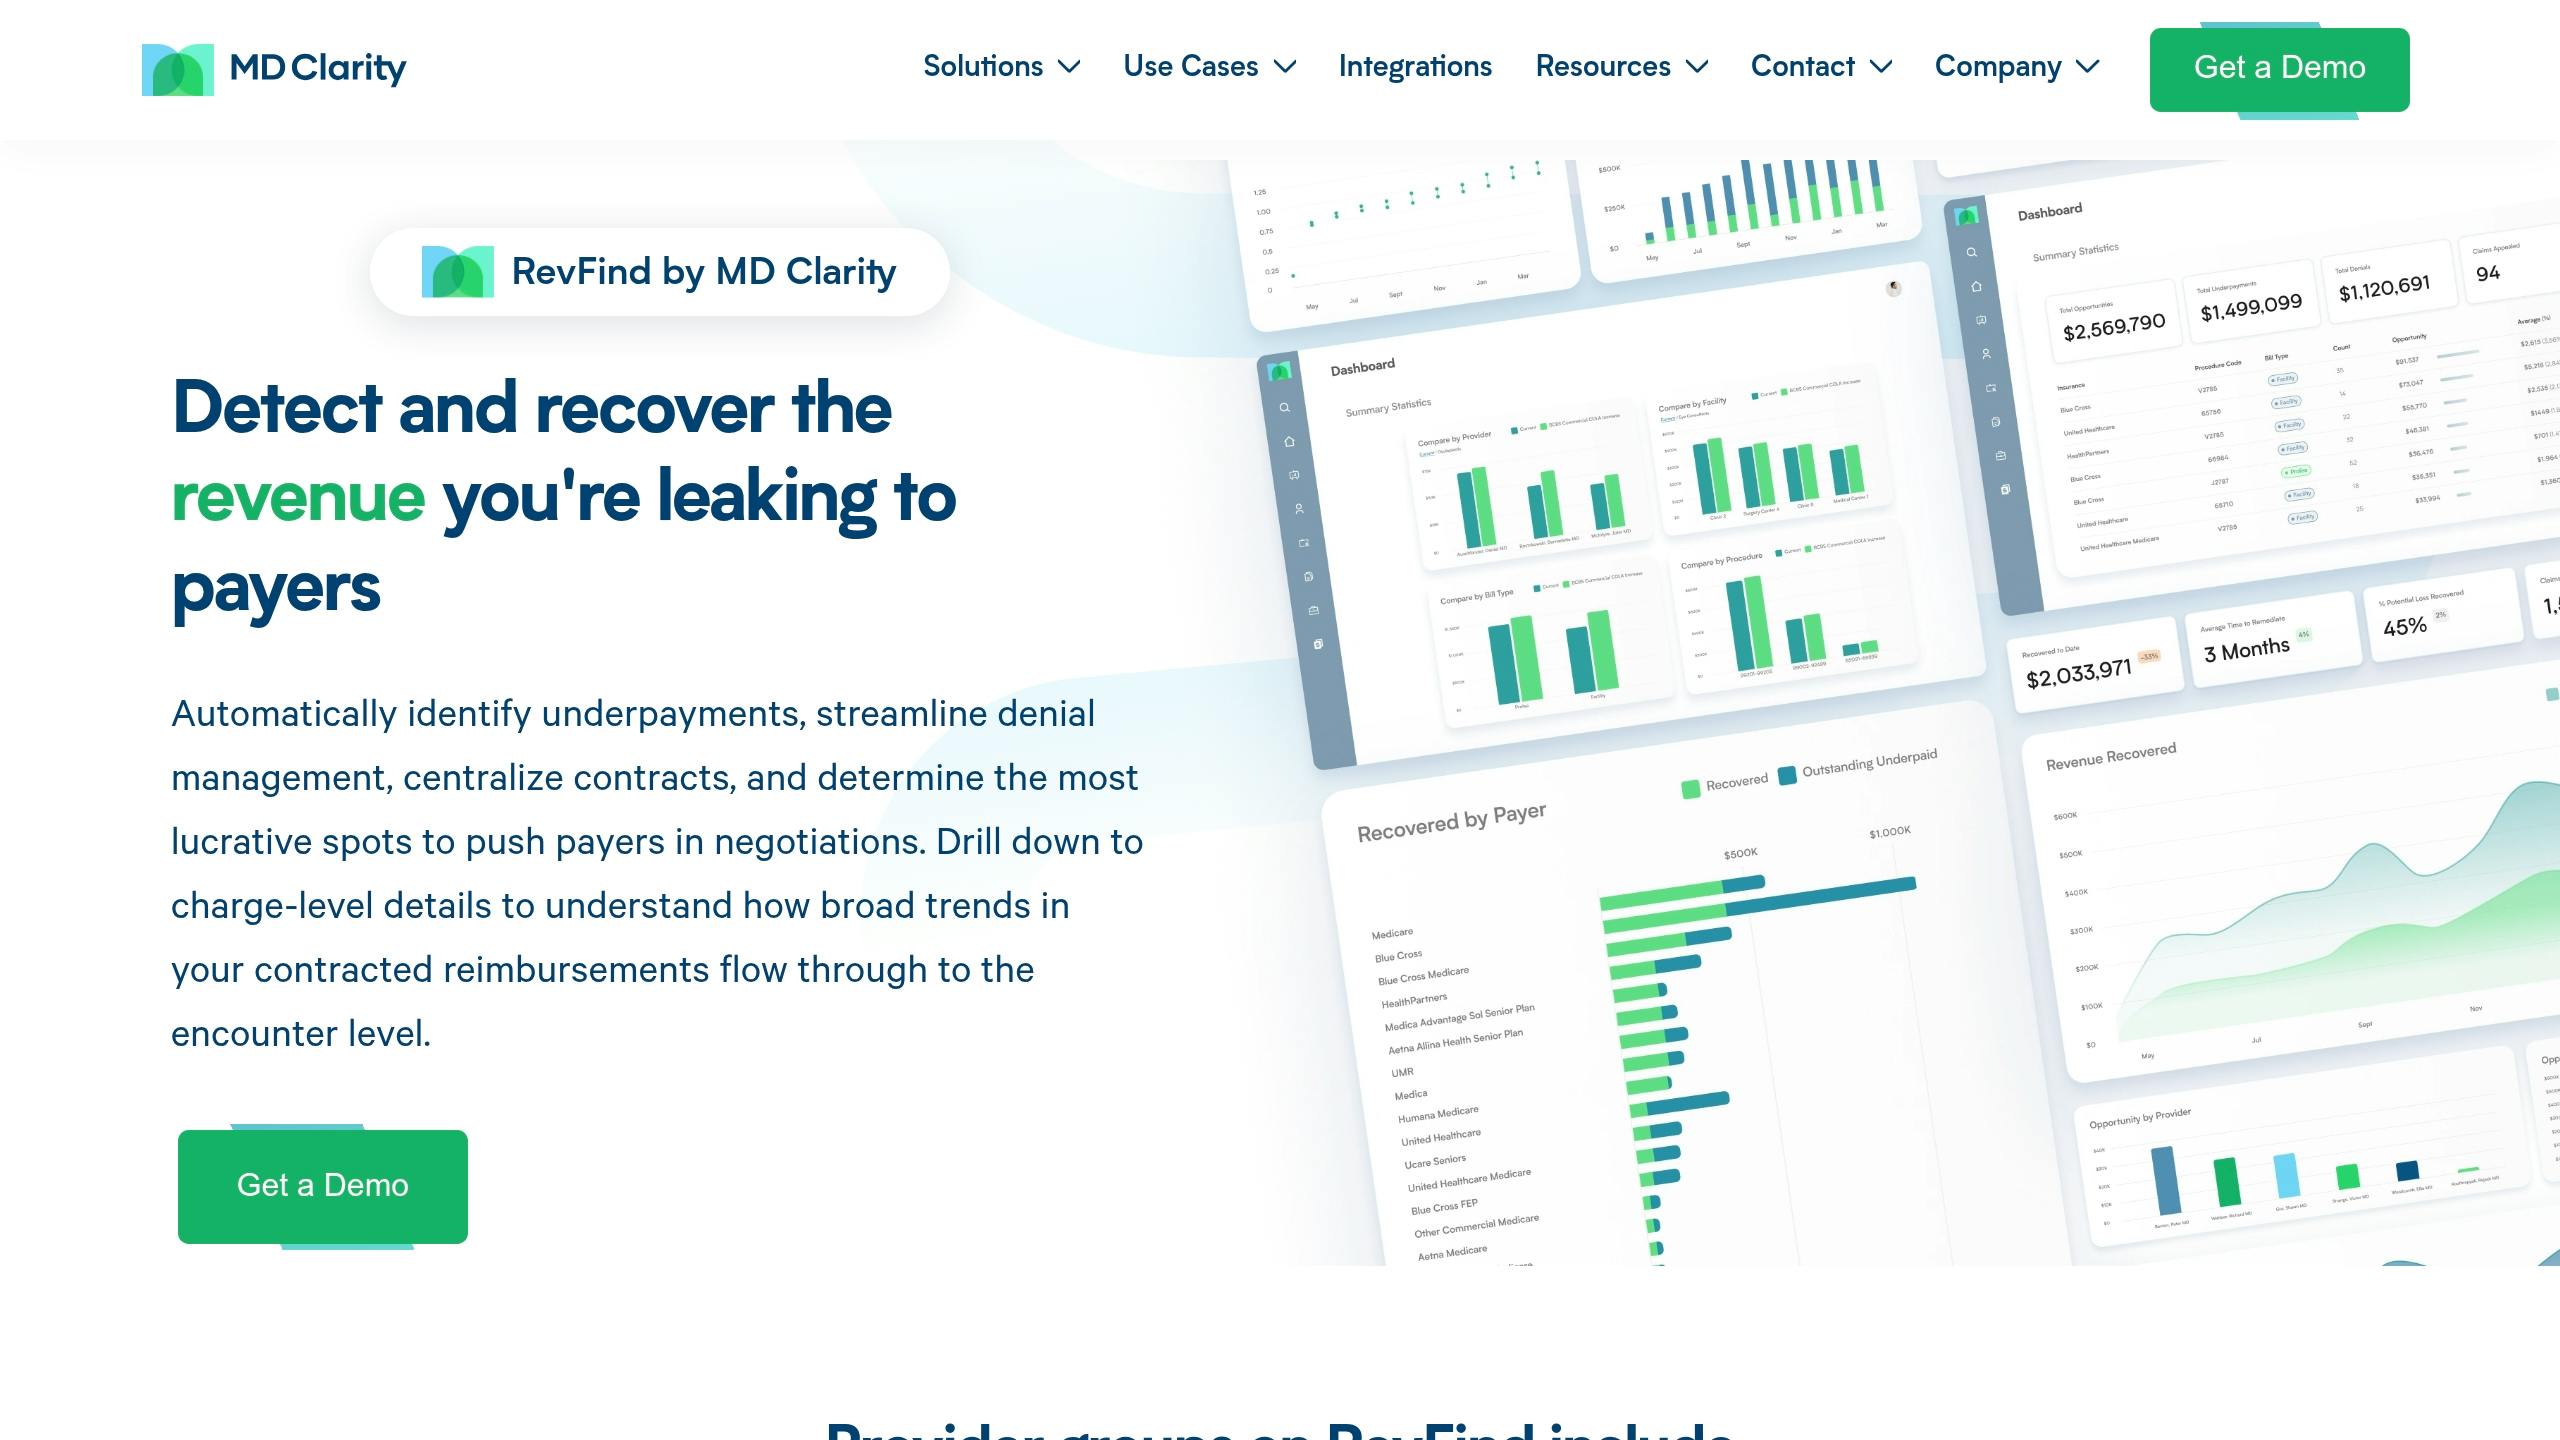
RevFind models payer adjudication at the charge-line level, so the variances it finds reflect contract logic, not just a simple fee check. That matters because its pricing engine applies rules such as GPCI adjustments, multiple-procedure reductions, and bundling logic before it flags a variance.[11][15]
Earlier tools tend to look at payment reconciliation in broader terms. RevFind goes much deeper, down to the individual charge line.
Contract Reconciliation
RevFind digitizes payer contracts into a searchable contract repository and reconciles payments at the CPT, HCPCS, modifier, and place-of-service levels.[11][12] It also includes patient responsibility in expected reimbursement calculations, which helps keep variance reports accurate.[11]
On the data side, it ingests HL7, FHIR, X12 835/837, and flat files from major EHR and PM systems.[12]
That line-level view helps teams catch variances soon after remits post.
Underpayment Detection
RevFind monitors remittances in real time and flags variances within hours of an ERA posting.[16] That timing gives teams a better shot at attaching contract language before the claim falls out of window.
MD Clarity says RevFind has detected more than $1.5 billion in total underpayments across over 150 million claims and remits.[13] In one example, Community Care Partners, an urgent-care MSO, recovered $160,000 from a single CPT code within three months of going live, then collected another $80,000 in the months that followed.[11][12]
Appeals Workflow
Once RevFind finds a variance, the next job is building the appeal file. It automatically routes the claim to a staff worklist with the specific contract language and ERA detail already attached.[11][12] It also generates payer-specific appeal packets that include the variance math and exact contract citations as support.[14][15]
To help teams focus their time, RevFind prioritizes open items by:
Dollar value
Payer response history
Claim age
[12][16]
If an organization doesn’t want to handle appeals in-house, MD Clarity also offers a fully managed recovery service in which its specialists pursue underpayments through collection.[11][17]
Behavioral Health Fit
RevFind’s line-item detail makes it a good fit for recurring therapy visits, mixed provider levels, and multi-location behavioral health groups. That’s especially useful when provider-level reimbursement differences and session-based CPT codes create repeat underpayment patterns across high claim volumes.[11][16][15]
5. R1 RCM
R1 focuses less on line-by-line variance spotting and more on enterprise-level recovery workflows, backed by human-reviewed contract parsing. In plain English: it pairs AI contract parsing with specialist review to recover underpayments across large health system workflows. R1 is ranked #1 by KLAS in Underpayment Recovery Services for 2026 and recovers more than $850 million per year for its clients.[18][21]
Contract Reconciliation
R1 uses AI to parse PDF contracts into a searchable repository. It pulls out contract terms and remittance rates for day-to-day RCM work.[18] Before any recovery work starts, clinicians, attorneys, and certified coders review the extracted terms.[18][19]
Underpayment Detection
Phare Flow links underpayment findings across remittances, denials, and outstanding claims so teams can manage payment variance and fix contractual underpayments.[18] The system checks 100% of claims with rules-based logic and flags discrepancies at the CPT and modifier level for professional billing.[18][20]
One large health system found $8 million in missed revenue in year one and nearly $25 million in total recoveries.[18]
Appeals Workflow
R1’s agentic AI takes on the early parts of the appeals process by segmenting data, gathering documentation, and drafting the appeal.[19] It cuts drafting time by 50%, bringing it down to about 20 minutes per appeal.[19] A clinician reviews the draft before submission, and Phare Flow manages the follow-up after that.[19] R1 reports an average denials overturn rate of 90% and a typical positive ROI within 90 days.[18][19]
Behavioral Health Fit
R1 fits large professional-billing groups working across commercial, Medicare, and Medicaid payers. Its materials do not call out behavioral health-specific workflows like group therapy billing or facility-based rates. So while it can be a strong match for large recovery operations, it appears less tuned for BH billing edge cases.
6. Experian Health
Experian Health’s Contract Manager and Contract Analysis tools compare actual reimbursement with contract terms so teams can spot underpayments as they happen. It has ranked #1 in Best in KLAS for Revenue Cycle: Contract Management for four straight years.[22][24] The big draw here is continuous monitoring, not a wait-until-month-end review.
Contract Reconciliation
Experian’s contract analysts maintain fee schedules, payment policies, and contract terms for the provider, including Medicare, Medicaid, and commercial payers.[22][24] The system prices claims before submission and then checks expected reimbursement against actual allowed amounts once remittance comes in.[23]
That’s a big deal. Payer policies shift often, and contract files can get stale fast. If your data is off, even small misses can turn into lost revenue.
Underpayment Detection
The platform compares actual payments to negotiated contract terms and uses Payer Alerts to watch policy changes across more than 1,900 payer websites, so teams can act before payments start slipping.[23][26]
That can lead to major recovery dollars. Northeast Health System recovered $16.1 million using Experian’s four-step contracting process.[22][23]
Appeals Workflow
Experian Health supports contract-based appeals with bulk claim handling. So instead of working claims one by one, staff can resolve hundreds on an individual basis in a much faster flow.
A good example is OrthoTennessee. It used the tool to process more than 600 claims in a single day that had been routed to the wrong network and reached an 86% appeal success rate in 2022.[23][25] That makes the platform a strong fit for teams that need contract monitoring and high-volume appeals in the same workflow.
Behavioral Health Fit
The platform is used by large health systems and medical groups, but the setup also works well for behavioral health. It supports payer-specific rules, shifting reimbursement models, and high-volume contract review, which lines up with behavioral health’s repeat visits, payer variation, and authorization-heavy workflows.[22][24]
It also integrates with most practice management systems and health information systems, which cuts down on manual handoffs.[22][24] For behavioral health providers, that matters when payer rules change faster than staff can update manual contract files.
Key Differences Between These Tools
These tools tackle different parts of the same problem.
The biggest gaps come down to how deep they go on contract logic, how they calculate reimbursement, and how much of the recovery work they take off your team’s plate.
When you line them up side by side, the split is pretty clear: some focus on broad RCM automation, while others go deeper into contract-intelligence workflows.
The clearest difference shows up in contract logic depth. BHRev is built for behavioral health payer contract review, claim scrubbing, underpayment recovery, and compliance across Medicaid, Medicare, and commercial plans. By contrast, many EHR and PM systems keep fee schedules in static tables. RevFind goes further by applying contract logic like escalators, carve-outs, and lesser-of clauses.[12]
Detection depth is the next big divider. BHRev leans into early underpayment detection through claim scrubbing and analytics. Deeper contract tools, on the other hand, tend to focus more on line-level reimbursement accuracy. That may sound like a small distinction, but it changes when issues get caught and how much manual review happens later.
Recovery support varies too. BHRev includes denial tracking and appeals in both full-service and targeted support models. RevFind is more centered on worklists, root-cause tracking, and appeal packet preparation.[12]
Staffing fit matters just as much as features. BHRev works well for groups that want either a purpose-built platform or an outsourced support model. Teams that need deeper contract modeling may lean toward a tool built around reimbursement logic and worklist-driven exception review.
Across all the tools reviewed, the main divide is how early they catch payment variance and how much appeal work they absorb. The simplest way to compare them is through contract logic, detection timing, and recovery support.
Tool | Contract logic | Detection timing | Recovery support | Best fit |
|---|
BHRev | Payer-specific rules for Medicaid, Medicare, and commercial plans | Early detection via claim scrubbing and predictive analytics | Denial tracking and appeals in full-service and targeted models | Behavioral health teams wanting flexible or outsourced RCM support |
Waystar | Remittance matching across 5,000+ payers; paper EOB conversion | Auto-reconciles 95%+ of payments; Medicare DRG-level review[2][3] | AI-drafted appeals with 1,000+ payer-specific forms[4] | High-volume mixed-payer operations needing scale |
FinThrive | 98%+ contract pricing accuracy; expert-managed contract loading[5] | AI flags variances and predicts repeat leakage[7] | Findings routed directly into claims workflows[7] | Outpatient and episode-based billing with complex contract terms |
MD Clarity RevFind | Line-level logic: GPCI, multi-procedure reductions, bundling[11] | Variance flagged within hours of ERA posting[16] | Auto-routed worklists with contract language and appeal packets[11][12] | Groups needing precise reimbursement logic and worklist-driven exception review |
R1 RCM | AI contract parsing with clinician and attorney review[18][19] | 100% claim review at CPT and modifier level[18][20] | Agentic AI drafts appeals; 90% overturn rate[18][19] | Large health systems running enterprise-scale recovery workflows |
Experian Health | Continuous monitoring across 1,900+ payer websites[23][26] | Pre-submission pricing checked against post-remittance actuals[23] | Bulk claim handling for high-volume contract-based appeals[23][25] | Large groups needing contract monitoring and high-volume appeals together |
Those differences shape the tradeoffs around cost, speed, and staffing burden. The next step is figuring out which tradeoffs matter most for your team: automation depth, recovery speed, or behavioral health fit.
Pros and Cons of Each Tool
The table below boils each option down to one clear upside and one main tradeoff for behavioral health underpayment prevention. The focus here is simple: what matters most for payer contract compliance, underpayment detection, and how fast teams can move on recovery work.
Tool | Pros | Cons |
|---|
BHRev | Average recovery of 32% on aged A/R after taking over billing [1] | More focused on behavioral health than on broader general health system use |
Waystar | Auto-reconciles 95%+ of payer payments across 5,000+ health plans [2] | No BH-specific workflow detail is provided |
Experian Health | Continuous contract monitoring with pre-submission pricing checked against post-remittance actuals [23] | No BH-specific workflow detail is provided |
The source set provided here does not give enough support for a dependable pros-and-cons summary for FinThrive, MD Clarity RevFind, and R1 RCM.
Conclusion
After looking at contract logic, detection timing, and recovery support, the right choice comes down to your payer mix, billing complexity, and the team you have in place.
Behavioral health groups that bill Medicaid, Medicare, or managed behavioral health carve-outs need BH-specific claim scrubbing, denial management, and underpayment recovery. That’s where BHRev fits. It’s built around the payer mix behavioral health providers deal with every day, not a generic billing setup.
Large, multi-site organizations with seasoned billing teams need enterprise-scale automation and cross-specialty infrastructure. Those teams usually need systems that can handle a lot of moving parts across locations, service lines, and payer contracts without things slipping through the cracks.
A few habits matter no matter which tool you pick:
Centralize contracts
Update fee schedules quarterly
Reconcile every payment at the claim level
Assign one owner to appeals
And one point is easy to miss: posted payments shouldn’t mean the work is done. They should trigger verification, not closure. The teams that close the underpayment gap fastest check every payment, not just every denial.
FAQs
How do I know if we have underpaid claims?
Compare actual reimbursements with the rates in your payer contracts to spot underpaid claims. Many practices check only a small portion of claims by hand, so missed underpayments are common.
BHRev helps you track payer performance with predictive analytics and live dashboards. It compares paid amounts with contracted fee schedules, flags discrepancies, and helps support payer contract compliance.
What should an RCM tool check before and after payment?
Before submission, an RCM tool should check claims against payer-specific rules to help cut down on denials. That means reviewing code combinations, modifiers, place of service, medical necessity, prior authorization triggers, and real-time eligibility, benefits, and coverage checks.
After payment, it should audit remittances line by line and compare paid amounts with expected reimbursement based on payer contracts and fee schedules. This helps spot underpayments, overpayments, and variance patterns.
When should behavioral health groups outsource RCM?
Behavioral health groups should think about outsourcing RCM when staffing gaps leave billing teams stretched thin or when in-house staff have a hard time with the details of behavioral health billing.
It also makes sense when shifting payer rules, medical necessity documentation, and authorization demands lead to denials, write-offs, cash flow problems, or payer compliance issues. BHRev offers AI-powered RCM outsourcing built for these situations.

